Around 5% to 15% of women of reproductive age have endometriosis. The diagnosis particularly affects women who still wish to have children. In the following text, our fertility specialist Dr Mann answers frequently asked questions from affected women.
- Can you get pregnant despite endometriosis?
- What can patients do to fulfil their wish to have a child?
- Do women with endometriosis have a higher risk of complications during pregnancy?
- What can women with adenomyosis who wish to have children do?
Endometriosis and the desire to have children: the key facts at a glance
With endometriosis, tissue from the uterus grows, for example, into the abdominal cavity or the ovaries. Possible consequences include adhesions and inflammation. However, there may also be no symptoms at all.
In principle, women with endometriosis can get pregnant, but their fertility is reduced by 50%. With a little patience or fertility treatment, many are ultimately able to fulfil their wish to have a child.
Patients have a higher risk of complications during pregnancy. The risk of miscarriage is increased by 75%.
If tissue from the uterine lining grows into the uterine wall, this is referred to as adenomyosis. Fertility is even more limited in this case, but in principle these women can also become pregnant.
Can you get pregnant despite endometriosis?
Many endometriosis patients fear that they will not be able to fulfil their wish to have a child. Although endometriosis patients are more often infertile than average, many women become pregnant despite the condition. Infertility is only diagnosed when pregnancy does not occur after 12 months of regular unprotected intercourse.
How high is the chance of getting pregnant with endometriosis?
In a woman with endometriosis, fertility is reduced by about half. Statistically, this means for those wishing to have children: for a 22- to 23-year-old endometriosis patient, the probability of becoming pregnant is 12.5% to 15%. For a healthy woman in this age group, it is 25% to 30%.
A pregnancy rate of around 12.5% to 15% is typical for a healthy 35-year-old. A 35-year-old with endometriosis, on the other hand, has a probability of 6.25% to 7.5% per cycle of becoming pregnant. For a healthy woman over 40, the pregnancy rate per cycle is 5% to 8%; with endometriosis, the probability decreases to 2.5% to 4%.
Why can endometriosis impair fertility?
In women diagnosed with “endometriosis”, tissue similar to the uterine lining grows outside the uterus, for example in the abdominal cavity or in the ovary. Although the endometriosis lesions are benign, they can cause severe pain, inflammation, cysts and adhesions. They can pose a mechanical obstacle to becoming pregnant. Even women with a mild course of endometriosis and few adhesions can be infertile. Why this is the case is still unclear. One possible explanation is inflammatory processes in the abdominal cavity, which can impair egg quality. In addition, the ovarian reserve is often reduced. This means that affected women have fewer eggs and enter the menopause earlier.
Incidentally, the size of the growths does not necessarily say anything about the fertility of those affected. Even small endometriosis lesions can lead to infertility, while even extensive adhesions may remain symptom-free. Endometriosis can lead to infertility, but it is not synonymous with it.
Fertility test for women
Are you affected by endometriosis and would like to find out how your fertility is? With our specially developed fertility tests, you can quickly and easily obtain meaningful information about your ovarian reserve and fertility. Choose between a convenient at-home test kit or a personal appointment on site!
Take the fertility testWhat can endometriosis patients do to fulfil their wish to have a child?
1. See a doctor
It is advisable to contact a fertility centre immediately for further clarification of the diagnosis. There, it will be determined whether endometriosis is really the reason for infertility, which is not always the case. It is also possible that endometriosis is only one of many factors affecting fertility. Other possible factors include hormonal imbalances and reduced sperm quality in the man. In fact, multiple factors often occur at the same time. For example, in one third of couples with an unfulfilled desire to have children, the fertility of both partners is impaired. The more factors come together and the less likely a pregnancy is naturally, the sooner treatment should begin. Endometriosis patients over the age of 35 in particular should not lose valuable time, as fertility continues to decline with increasing age.
2. Monitor your cycle or start treatment
Especially for younger patients, it does not have to be an extensive therapy with assisted reproduction right away. Depending on the initial situation, it may be sufficient to monitor the cycle first. Identifying fertile days and having intercourse at the right time increases the chances of becoming pregnant naturally.
For older patients, it is important to lose as little time as possible. In these cases, we recommend moving more quickly to a therapy such as IVF. The same applies to women whose fallopian tubes are no longer patent. If the pathway between the ovaries and the uterus is blocked, assisted reproduction is the only way to achieve a pregnancy. Learn more about the costs of assisted reproduction.
Incidentally, implantation of the egg is not a problem for most patients. This is suggested by a study conducted with egg donors. When eggs from healthy women were implanted in endometriosis patients with an unfulfilled desire to have children, the likelihood of implantation did not worsen. The results were very different when the donor had endometriosis and the recipient did not. In this case, implantation of the eggs was significantly poorer. This shows that egg quality is an issue for endometriosis patients, but implantation in the uterus is not.
3. Live healthily: nutrition tips & home remedies for endometriosis patients who wish to have children
Various nutrients are currently being discussed as potentially having a positive effect on egg quality. These include vitamin D, coenzyme Q10 and folic acid. In fact, we have had similar experiences at our fertility centre: when we carry out several IVF treatments for an endometriosis patient who adjusts her nutrient intake in the meantime, we sometimes see improvements. It may therefore be worthwhile optimising your diet before pregnancy. It is also advisable to stop smoking, as tobacco consumption has a negative effect on ovarian reserve. Also avoid being underweight or overweight, have general illnesses treated and exercise regularly. All of this helps you get fit for pregnancy.

How many women become pregnant after endometriosis surgery?
This question was investigated by a study from France involving 55 patients with deep endometriosis lesions. They were all the same age and were treated by the same doctor. Thirty-six of them wanted a child. In fact, there were 29 births in the following years. Even 74% of the women succeeded, despite having tried unsuccessfully to become pregnant for at least a year beforehand. In about half of the cases, pregnancy occurred naturally; in the other half, as a result of fertility treatment. Young age, normal weight and a low severity of endometriosis favour the onset of pregnancy, according to another study.
Do women with endometriosis have a higher risk of complications during pregnancy?
According to a study, those affected more often give birth to small and underweight babies. Newborns are also more often born prematurely. In addition, according to a large study, patients have a 75% higher risk of miscarriage. The risk of a pregnancy outside the uterus was three times as high as in women without endometriosis. The cause of these complications could be inflammation in the abdominal cavity and changes in the uterus.
What can women with adenomyosis who wish to have children do?
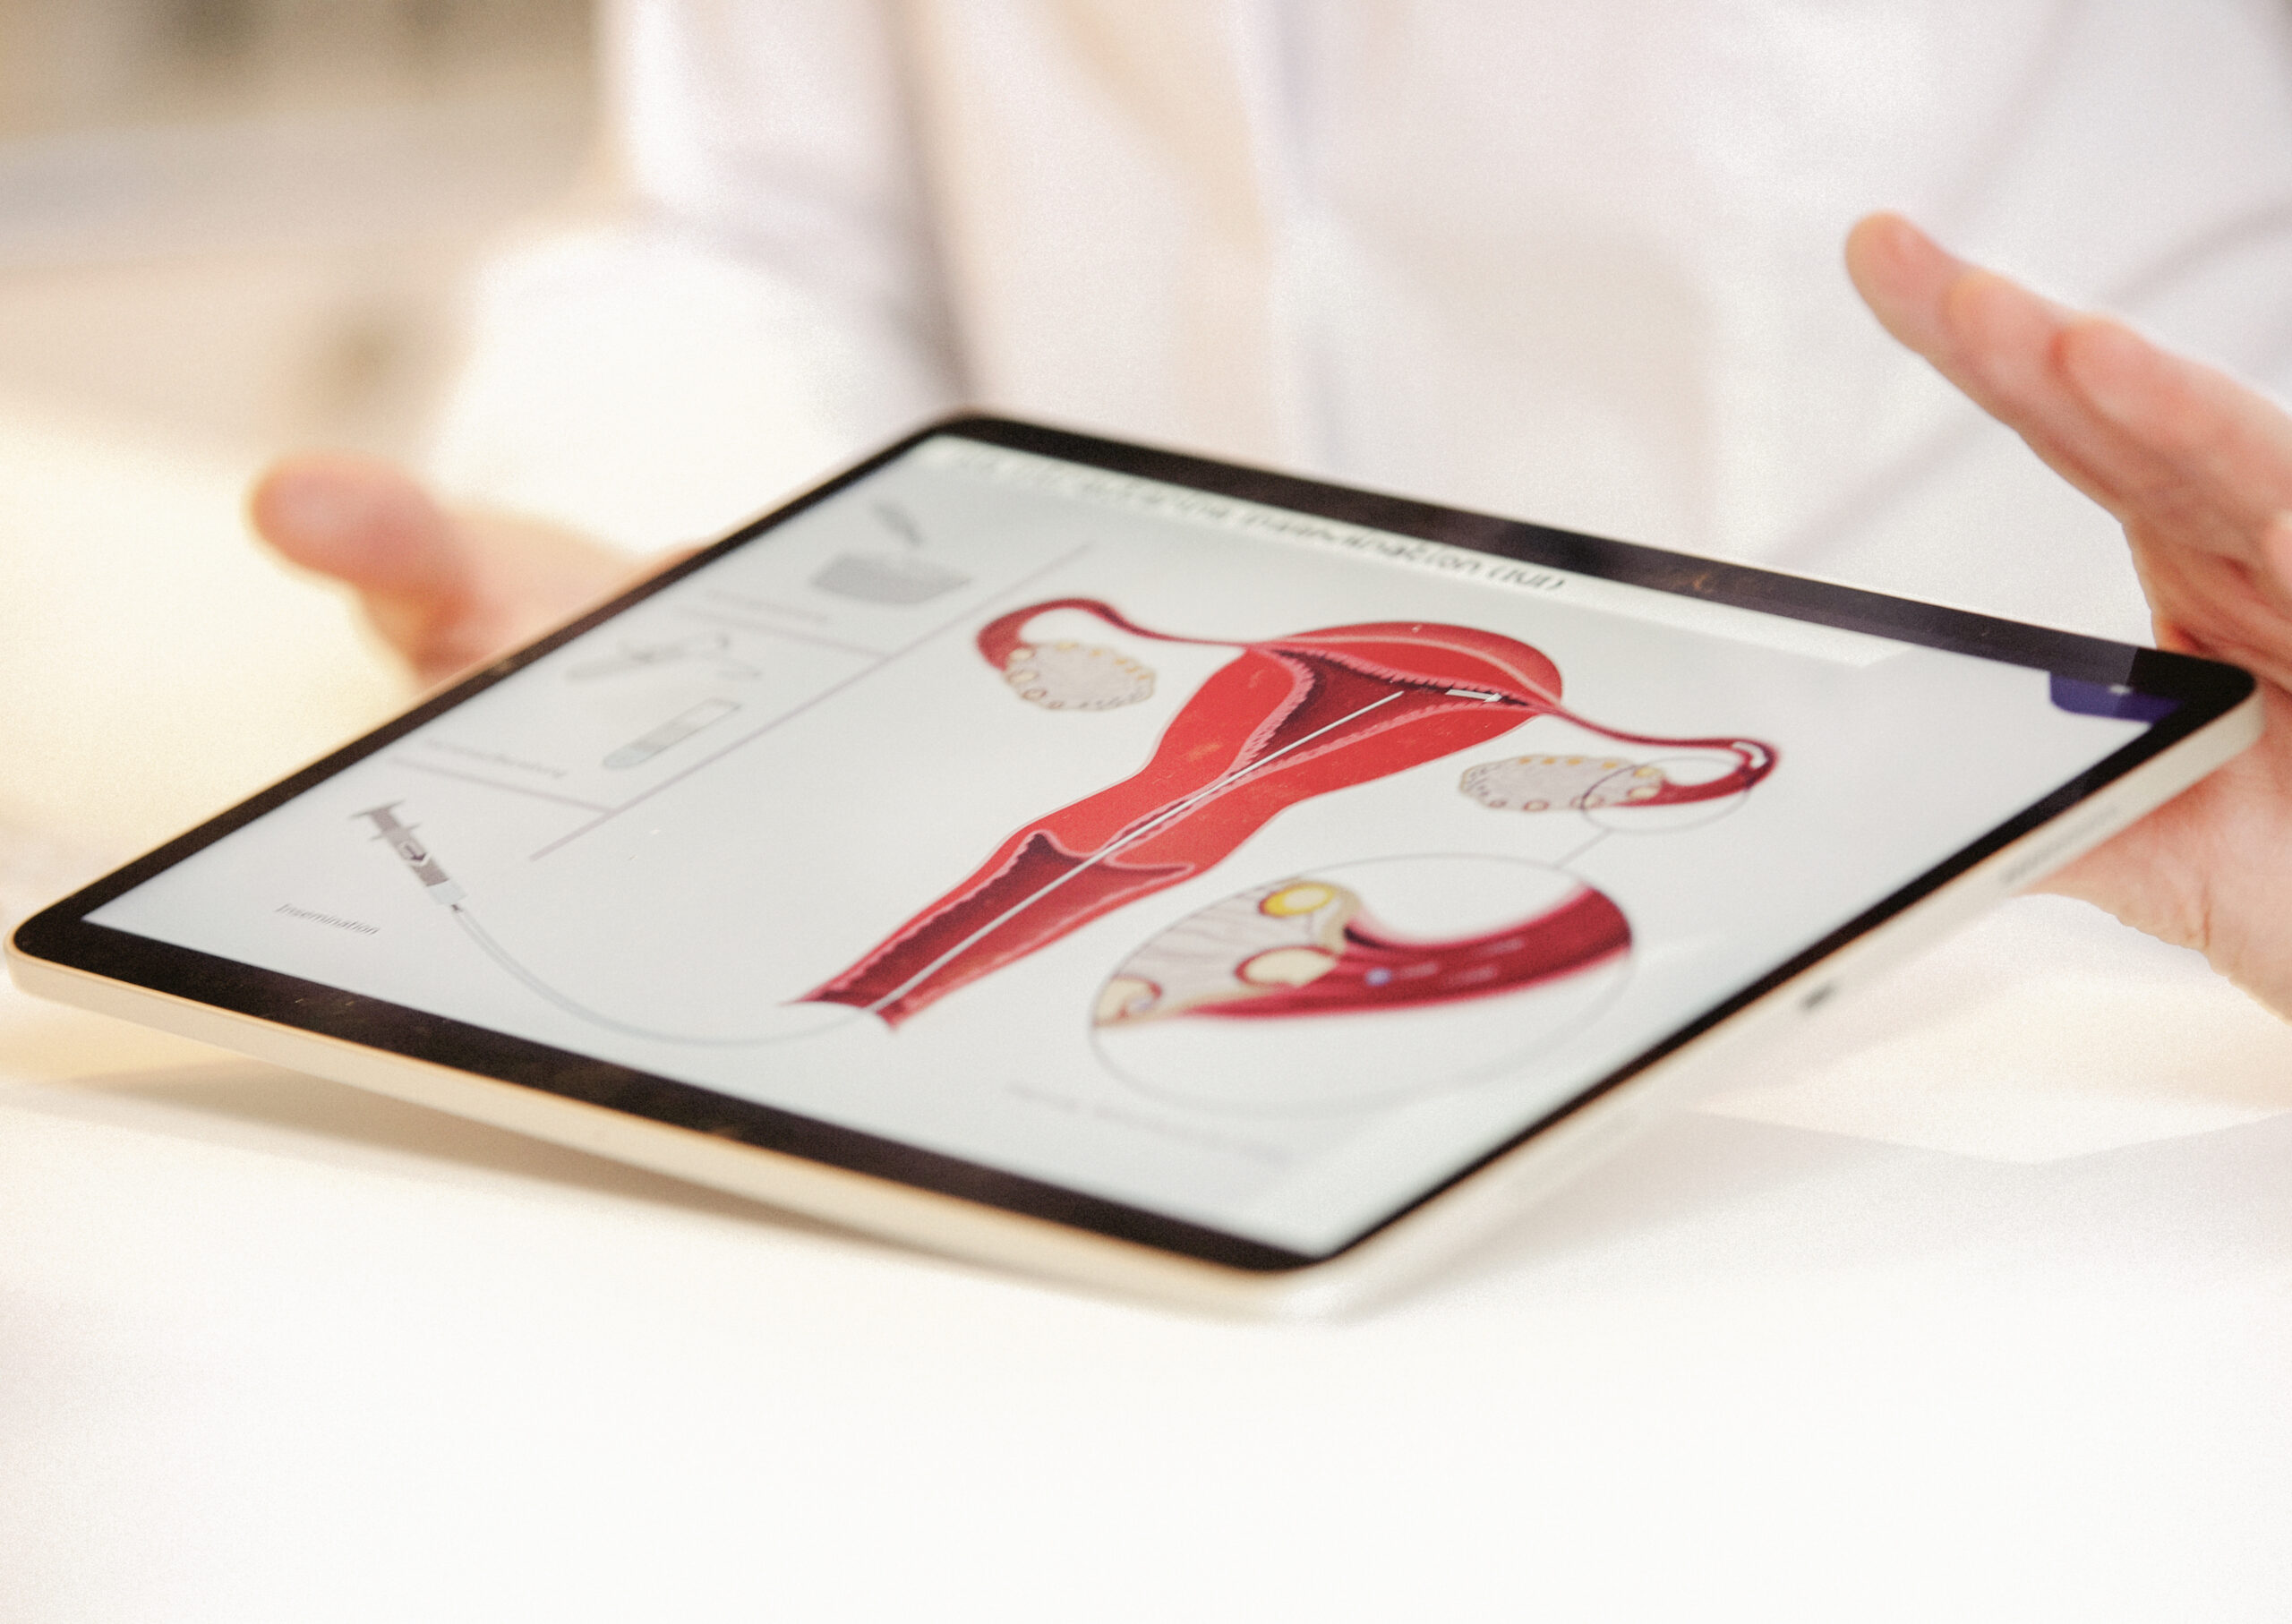
Adenomyosis is essentially endometriosis in the uterine wall. In this case, tissue from the uterine lining grows into the muscle tissue of the uterus. Implantation of the egg is then significantly more difficult. Without adenomyosis, the probability of implantation is 40%; with adenomyosis, only 20%. Nevertheless, affected women also have a chance of becoming pregnant.
Surgery is generally not possible, as the tissue usually grows diffusely and is difficult to remove. In addition, there is a risk of injuring the uterus during surgery. Surgery only makes sense in individual cases, when a single, clearly defined lesion needs to be removed.
Hormone therapy may be an alternative. It may be able to shrink the adenoma, which in turn could increase the chances of pregnancy.
Once pregnancy has occurred, the miscarriage rate is significantly higher than in healthy women. Those affected should therefore be especially careful to follow the recommendations that are advised to all pregnant women.
This includes, for example:
- stop smoking
- reduce coffee consumption to two cups a day
- avoid alcohol as much as possible
- attend regular prenatal check-ups
This can at least reduce the risk of miscarriage somewhat. Even though women with endometriosis or adenomyosis face challenges when trying to conceive, we would like to encourage everyone affected. Some become pregnant naturally, others with specialist medical support. Do not hesitate to seek help, and keep going!